When Government Sets The Price: The Reference-Pricing Era
The price floor for U.S. drugs is increasingly set abroad, here's how reference pricing is changing pharma's commercial playbook.


Introduction
For most of pharma's history, price was something a company decided, then defended. A manufacturer set a list price, negotiated rebates with payers, and commercial teams built their entire pitch around value, outcomes, and competitive positioning within that self-determined range.
In 2026, that starting assumption is breaking down. For a growing share of the U.S. market, the government isn't just regulating prices anymore. It's setting it, using prices paid in other countries as the benchmark.
This is a genuinely different selling environment, and it's one commercial teams are only just beginning to fully operate in. Understanding how it works, and what it changes, is quickly becoming a core part of market strategy rather than a side conversation for the policy team.
How Government-Set Reference Pricing Actually Works Right Now?
There isn't just one policy driving this. There are several, moving on overlapping timelines, and commercial teams need to understand the difference between them because each one changes the sales conversation differently.
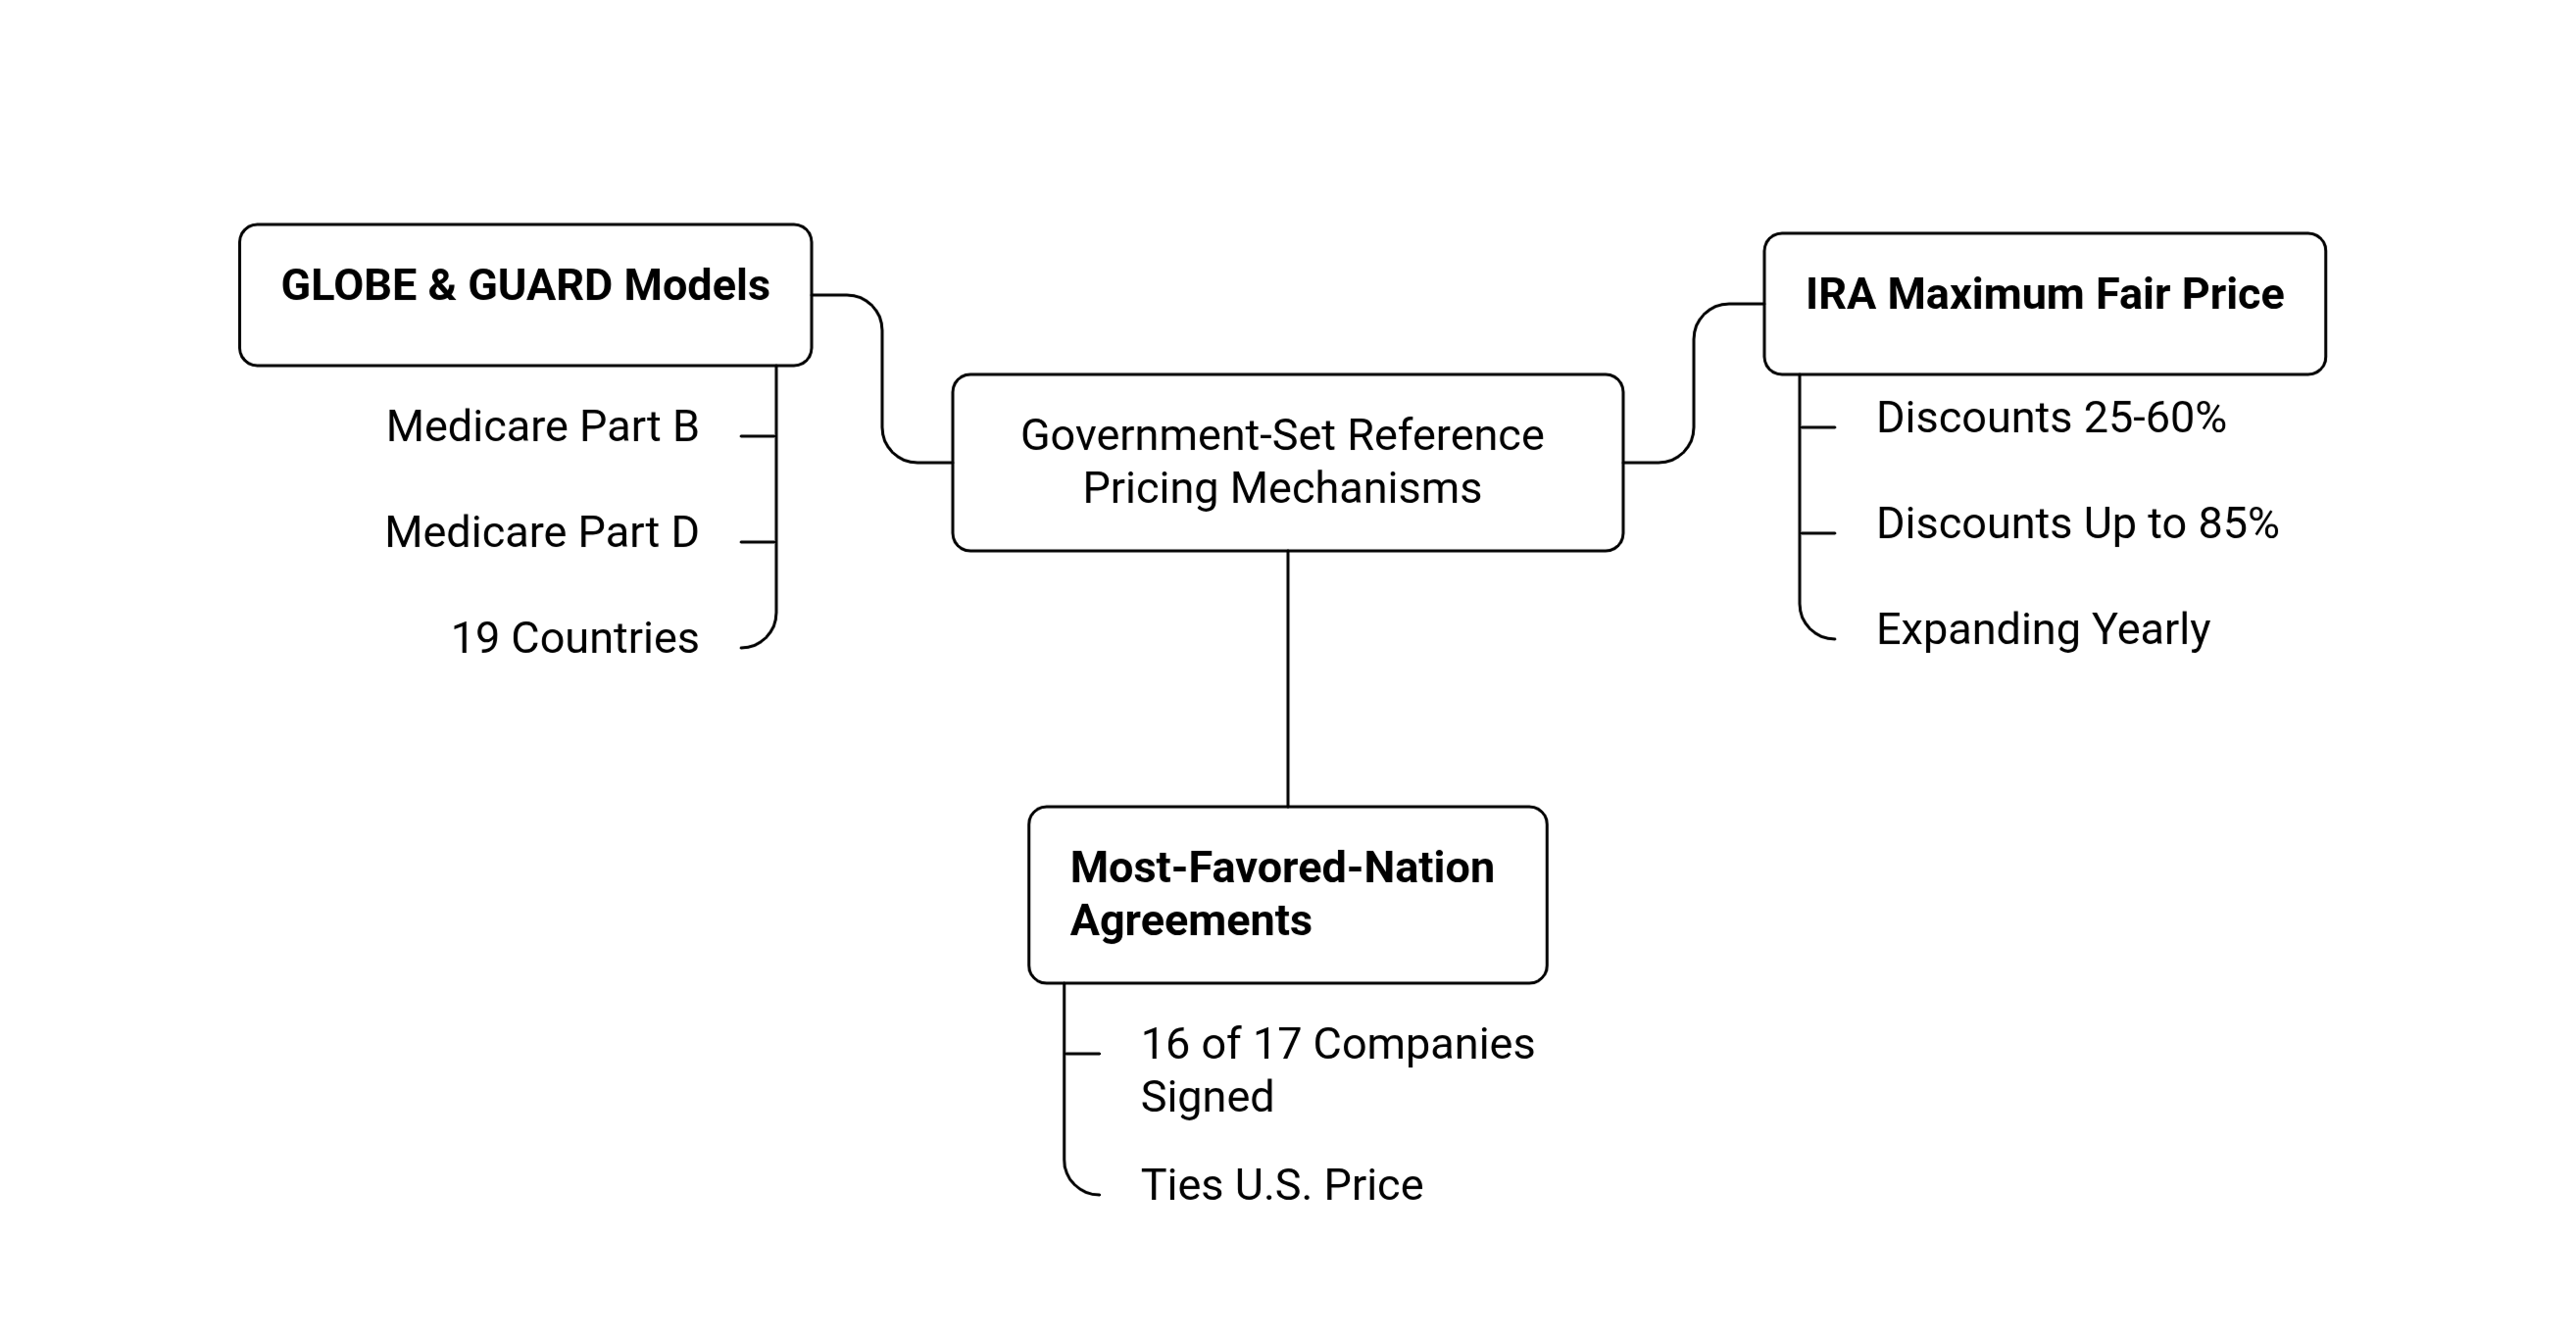
1) The Inflation Reduction Act's Maximum Fair Price: This is the original mechanism, allowing Medicare to directly negotiate prices on selected drugs for the first time in the program's history. The first round of negotiated prices took effect on January 1, 2026, and the discounts have been steep, typically in the 25% to 60% range off list price, occasionally reaching as high as 85% for certain products. CMS will keep expanding the list, negotiating 15 more drugs for 2027, another 15 for 2028, and 20 per year starting in 2029.
2) Most-Favored-Nation Pricing Agreements: Separately, the current administration has pushed manufacturers to sign voluntary MFN deals tying U.S. prices to whatever those same companies charge in other developed countries. By February 2026, sixteen of the seventeen largest pharmaceutical companies had signed on, agreeing to Medicaid price parity, MFN pricing on new launches, and participation in a forthcoming government pricing portal, in exchange for tariff relief and friendlier regulatory treatment.
3) The GLOBE & GUARD Models: CMS has proposed two formal international reference pricing models. GLOBE would apply to Medicare Part B drugs starting in October 2026, and GUARD would apply to Part D drugs starting in January 2027. Both would benchmark U.S. prices against a basket of nineteen other countries, including Canada, Japan, Germany, France, and the UK, and cap Medicare payment at a set percentage above the lowest price found among them.
Layered together, these three tracks point in the same direction: less room for a manufacturer to set its own U.S. price independent of what it charges everywhere else in the world. And that shift touches Medicaid, Medicare Part B, Medicare Part D, and increasingly the reference points that commercial payers use in their own negotiations too.
Why This Isn't Just A Pricing Team Problem?
It's tempting to treat reference pricing as something that lives entirely in market access and government affairs, resolved before a product ever gets to commercial launch. That's no longer accurate. A few reasons this now sits squarely inside the commercial function:
The sales pitch itself has to change. When price is a fixed reference point rather than a negotiated outcome, the conversation with a payer or health system shifts away from "let's find a number that works" toward "here's the value story that justifies staying above the floor for as long as possible."
Net price and rebate strategy no longer mean what they used to! Industry analysts at a recent AMCP session noted that higher rebates may no longer signal better value once reference pricing compresses list prices into a narrower band, and that contract assumptions built on the old rebate-centric model are unlikely to hold through at least 2027.
Launch sequencing decisions carry pricing consequences. Because MFN pricing looks at what a company charges in other countries, a decision to delay or skip a launch in a lower-priced market can directly affect the reference price used to set the U.S. floor, turning a market access team's country-by-country launch plan into a pricing lever.
Formulary and access conversations happen on a shorter cycle. With new negotiated prices and reference benchmarks rolling in every year, health plans and pharmacy benefit managers are recalibrating formularies more frequently, which means commercial teams need fresher data and faster response cycles than the old annual contracting rhythm allowed.
None of this is theoretical. One clear example: at least five of the fourteen companies that signed MFN agreements are still raising list prices on other products in January 2026, a reminder that these deals are narrow and product-specific, not a blanket reset. Commercial teams selling a product inside an MFN agreement and a product outside one, often within the same portfolio, are now operating two different pricing logics at once.
Reference pricing isn't the only force reshaping how pharma sells, direct-to-consumer pricing is redrawing the commercial playbook too.
→ Read: What Direct-To-Consumer Pricing Changes For Pharma Teams
What Actually Changes For The Commercial Playbook?
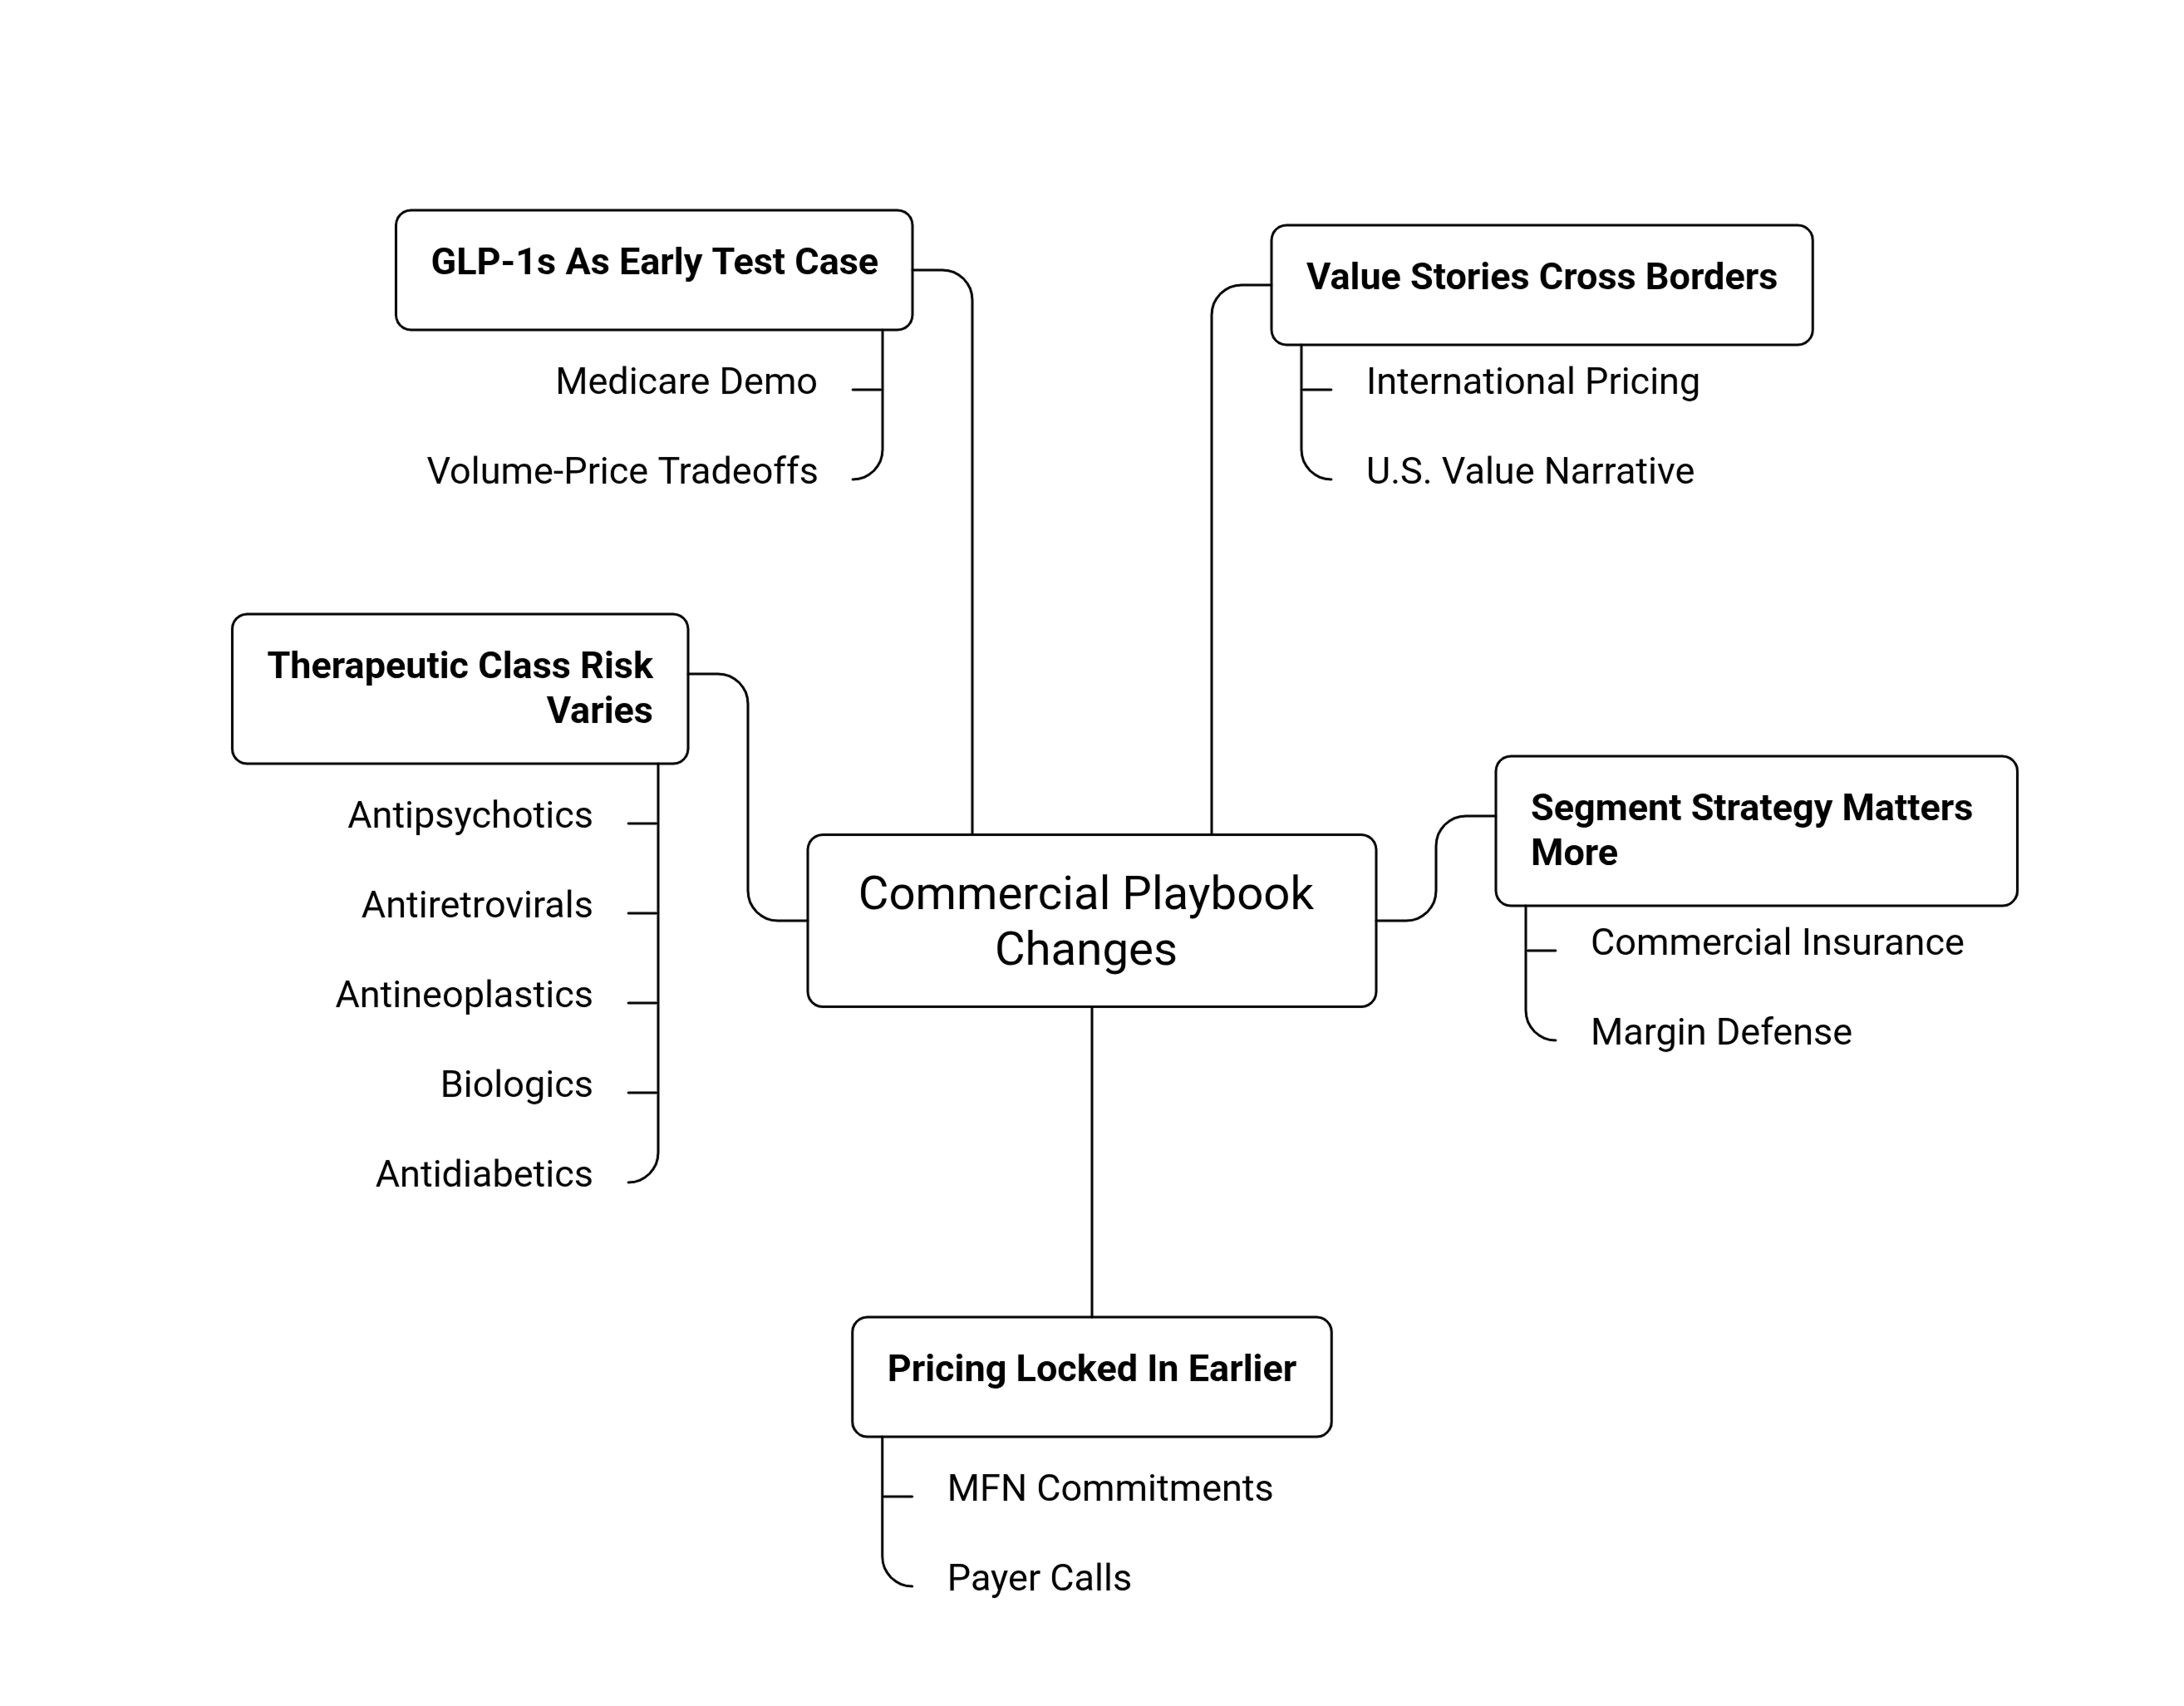
Selling into a reference-priced market requires a few real shifts in how commercial teams plan and operate:
1) Value stories need to travel across borders, not just across payers. If a discount agreed to in Germany or Japan can eventually show up as the U.S. Medicare price, then a commercial team's international pricing strategy and its U.S. value narrative are no longer separate workstreams. They need to be built together.
2) Segment strategy becomes more important, not less. With Medicare, Medicaid, and MFN-linked cash pricing all converging toward a lower reference point, the commercial insurance segment, still roughly 155 million Americans who see no direct benefit from either the IRA negotiations or the MFN deals, becomes a relatively more important place to build differentiated value and defend margin.
3) New product launches need a pricing strategy before the first payer call. Because MFN commitments apply to new launches for companies that have signed agreements, pricing strategy has to be locked in earlier in the product lifecycle than commercial teams are used to, often before full competitive and access data would normally be available.
4) Therapeutic class matters more in planning. Government modeling has flagged specific categories, including antipsychotics, antiretrovirals, antineoplastics, anti-inflammatory biologics, and antidiabetics, as facing the steepest projected impact, since Medicaid net prices in these classes are currently estimated at two to three times the international benchmark. Teams in these categories should expect the most pressure first.
5) GLP-1 and high-demand categories are becoming an early test case. A new Medicare demonstration launching July 2026 will offer beneficiaries GLP-1 access at a flat $50 monthly copayment, outside the standard Part D benefit, giving commercial teams in this category a live preview of how volume and access can expand even as list price compresses.
The Leadership Question: Who Actually Owns This Now?
Reference pricing forces a genuine organizational question that a lot of companies haven't fully answered yet: who is accountable for a pricing strategy that's set, in part, by decisions made in other countries and by government agencies rather than by the company itself?
A few patterns are emerging among companies handling this well:
Global pricing and U.S. commercial teams are being pulled into the same room earlier. A pricing decision in one country can no longer be treated as isolated from U.S. strategy, so companies are building shared governance between global market access and domestic commercial leadership rather than letting each operate independently.
Legal and contracting expertise is becoming a commercial skill, not just a support function. Existing licensing and distribution agreements often include their own most-favored-pricing clauses, meaning an MFN deal with the government can unexpectedly trigger price-change obligations to a completely different commercial partner. Commercial leaders need enough fluency here to spot that risk before it becomes a legal problem.
Scenario planning is replacing static forecasting. With GLOBE, GUARD, and IRA negotiation rounds all landing on different timelines through 2029, teams that build a single fixed price forecast are likely to be wrong within a year. The companies managing this best are running multiple pricing scenarios side by side and updating them as each policy track moves.
A single accountable owner is helping companies move faster. Much like the supply chain and tariff challenges reshaping manufacturing decisions, reference pricing is pushing some organizations to name a specific leader, often within global pricing strategy or market access, who can make fast calls when policy changes hit mid-negotiation with a payer.
Pricing isn't the only qualification shifting for commercial teams, where a drug is made is becoming one too.
→ Read: Supply-Chain Geography is Now A Pharma Commercial Qualification
Wrapping It Up!
The White House has projected close to $600 billion in savings over ten years from its MFN framework, and independent economists are already debating whether that number is realistic or whether it understates the ripple effects on innovation incentives and access.
That debate matters, but for commercial teams, the more immediate reality is simpler: the floor under U.S. drug pricing is increasingly being set somewhere else, by someone else, and the job of selling has to adapt to that fact rather than wait for it to resolve.
Companies that treat reference pricing as a temporary policy fight to be won or lost in Washington are likely to keep getting surprised by each new negotiation round, each new country-level price change, and each new formulary recalibration.
Companies that treat it as a permanent feature of the market, one that has to be built into value stories, launch sequencing, contract language, and organizational ownership from the start, are the ones positioned to keep growing even as the price ceiling keeps moving.
Either way, the commercial teams that come out ahead in this environment will be the ones who understand the reference price isn't a constraint to work around. It's the new starting line.
FAQs
1. What Is Reference Pricing In The Pharmaceutical Industry?
Reference pricing is a system where drug prices in one market are influenced by prices paid in other countries or regions. In the U.S., emerging government policies are increasingly using international prices as benchmarks, giving manufacturers less freedom to set prices independently.
2. How Is Government-Set Pricing Changing Pharma Sales?
It is shifting the sales conversation from negotiating a price toward proving product value. Commercial teams now need stronger evidence around clinical outcomes, patient benefits, and overall value to justify pricing and protect margins.
3. Which U.S. Policies Are Driving Reference Pricing?
Several policies are shaping the market, including the Inflation Reduction Act's Medicare drug price negotiations, Most-Favored-Nation pricing agreements, and proposed GLOBE and GUARD models. Together, these initiatives are increasing the influence of international drug prices on U.S. pricing.
4. Why Do Global Pricing Decisions Matter More For U.S. Pharma Teams?
Prices set in countries such as Germany, Japan, Canada, France, and the UK can influence international reference benchmarks. As a result, decisions about launch timing and pricing in other countries can have a direct impact on a drug's potential U.S. price.
5. What Should Pharma Commercial Teams Do To Prepare For Reference Pricing?
Teams should bring global pricing, market access, legal, and commercial functions closer together. They should also use scenario planning, strengthen value-based selling, review contract terms, and consider pricing implications early in the product launch process.
Reporting on the science, business and regulation shaping the pharmaceutical industry.
More in Pharma Marketing
All articles →
The Importance of Personalization in Pharmaceutical Marketing Campaigns

The Power of Storytelling in Pharma Marketing: Engaging Customers with Your Brand

Discussion